


Oura, Whoop, Apple and Samsung all want inside the health care system. The billing rules say a wellness device does not get paid.
The short version: the wearable industry spent a year fighting the FDA for the right to be classified as a general wellness product, and won that fight in January 2026. Medicare pays for remote patient monitoring only when the device meets the FDA definition of a medical device. The victory sealed the category out of the payment layer it keeps saying it wants to join.
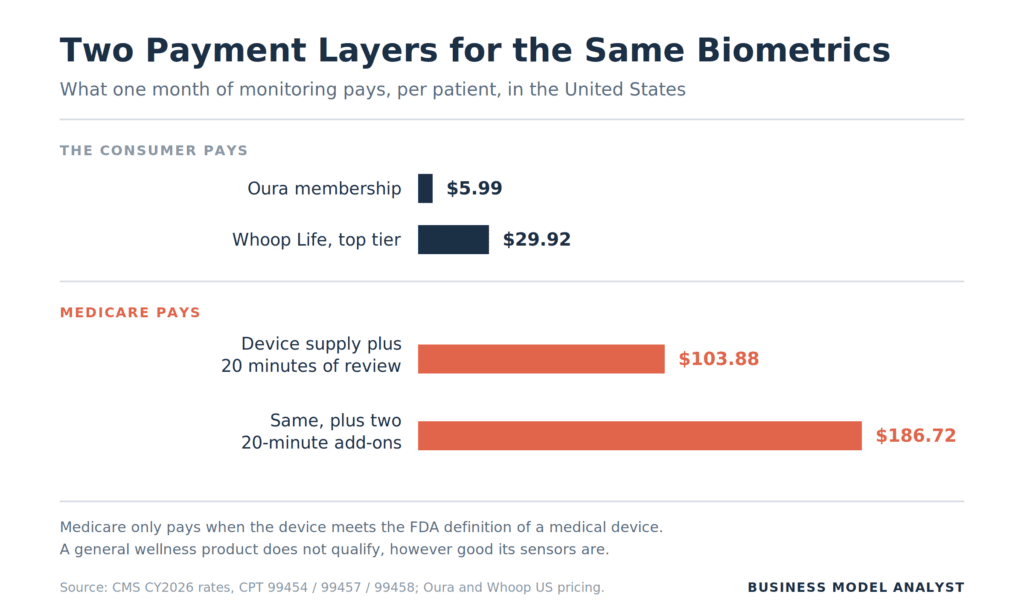
A primary care doctor can bill Medicare roughly $104 a month to monitor a hypertensive patient using a $40 connected blood pressure cuff. She cannot bill a dollar for the $549 smart ring on that same patient’s finger, or the band on the wrist. The ring has better sensors, a nicer app and a machine learning model behind it. The cuff has a classification.
What Happened
The New York Times DealBook laid out the state of the wearables war this week, and the picture is one of everyone sprinting toward the same door. Apple has partnered with Epic Systems. Samsung bought a hospital integration platform. Google launched a health app meant to consolidate Fitbit data with medical records. Oura took investment from Dexcom, the continuous glucose monitor maker, and its CEO Tom Hale would rather you call the ring a health intelligence platform than a fitness tracker.
IDC analyst Jitesh Ubrani gave the piece its thesis in one line: “The end goal is to be part of the medical ecosystem.”
He is right about the goal. The reporting, like most reporting on this category, treats the goal as a distribution problem. Get the data into Epic, get the doctor to look at it, get the hospital to recommend the device. That framing skips the only question that decides whether any of it becomes revenue: when a wearable ends up in a clinical workflow, who writes the check, and against which line item?
Right now, for the entire consumer wearable category, the answer is nobody, and there is no line item.
The Backstory
In July 2025, the FDA sent Whoop a warning letter over Blood Pressure Insights, a feature that estimated daily systolic and diastolic readings from blood flow patterns captured during sleep. The agency’s position was that blood pressure is a clinical vital sign, so the feature made the band a medical device.
Whoop CEO Will Ahmed refused to pull it and argued the feature belonged under the general wellness exemption created by the 21st Century Cures Act. He also lobbied. On January 6, 2026, FDA Commissioner Marty Makary announced an updated version of the agency’s General Wellness policy, which allows optical sensors to estimate parameters like blood pressure, blood oxygen and heart rate variability without triggering device regulation, as long as the outputs serve wellness purposes and the company makes no diagnostic claims. On June 17, the FDA closed out the Whoop warning letter.
Two details in that sequence went almost entirely unreported, and both cut against the celebration.
Whoop did not simply outlast the agency. It changed the product and the labeling, and the FDA’s closeout letter says so directly. The letter also states that it applies to the modified feature and to nothing else the company sells. That is not a precedent. It is a per-feature waiver with the company’s name on it, and the next feature starts the conversation over.
The Plan
Watch what these companies have actually bought, and a pattern shows up fast.
| Company | What it acquired or built | What it still does not have |
|---|---|---|
| Samsung | Xealth, closed October 2025. Reaches 500-plus US hospitals, 30-plus health systems, 70-plus digital health partners | A billing code for Galaxy Watch or Galaxy Ring data |
| Apple | Health Records integration with Epic | Any reimbursement pathway for Apple Watch metrics |
| Google Health app, launched May 2026, combining Fitbit data with medical records | Payer coverage for Fitbit devices | |
| Oura | Dexcom investment, US manufacturing, a $96 million Defense Health Agency contract | Medical device status for the ring |
Every one of these purchases buys plumbing. Xealth sits inside the electronic health record and lets a clinician push digital tools to a patient. Epic integration lets a doctor see the data. Google Health puts records in one app.
Plumbing moves data. It does not move money. A hospital that can see your Oura readings inside Epic still has no mechanism to bill anyone for looking at them, and a hospital that cannot bill for an activity treats that activity as charity or marketing.
The Business Model Angle
Medicare has paid for remote physiologic monitoring since 2019, and the 2026 fee schedule expanded it. The stack looks like this:
| Code | What it covers | 2026 national average |
|---|---|---|
| 99453 | Device setup and patient education, once per episode | $21.71 |
| 99454 | Device supply plus transmission, 16-plus days of data | $52.11 |
| 99445 | Same supply, for 2 to 15 days of data (new for 2026) | $47.00 |
| 99457 | First 20 minutes of monthly management | $51.77 |
| 99470 | First 10 minutes of management (new for 2026) | $26.05 |
| 99458 | Each additional 20 minutes | $41.42 |
CMS added the two new codes on January 1, 2026, killing the old 16-day floor and the 20-minute floor that kept lighter-touch patients out of the program. Providers now have a wider net.
Read the eligibility rule attached to those codes, though, and the wearable industry falls straight through it. The device has to meet the FDA definition of a medical device, and the data has to upload to the clinician automatically. Consumer wellness trackers fail the first test by design, because their makers spent the last year lobbying to fail it.
The gap explains a survey result that landed in July and deserved more attention than it got. The American Medical Association polled 2,222 physicians across the US, Canada and Europe. Some 97% said they would review health data collected by a wearable. No more than 6% in any country had integrated that data into their practice. Doctors named regulatory hurdles and missing reimbursement as the reasons.
Willingness is at 97%. Adoption is under 6%. That 91-point gap is not a technology problem, an accuracy problem or an AI problem. It is an invoicing problem, and no amount of sensor improvement closes it.
Dexcom, which put money into Oura, runs the cleanest natural experiment in the industry, because it operates on both sides of the line with the same underlying sensor platform.
Its G6 and G7 monitors require a prescription and are reimbursed by 97% of US commercial insurers, by Medicare nationally, and by Medicaid in most states. That business produced $4.662 billion in 2025 revenue, up 16%, with 2026 guidance of $5.16 billion to $5.25 billion.
Its Stelo sensor is the same technology sold over the counter for cash: $99 for a 30-day supply, or $89 on subscription. In its first four months, Stelo pulled in $22 million from more than 140,000 users. Two years on, Dexcom still does not break out Stelo revenue as a separate line for investors.
Same company. Same sensors. One side is a $4.6 billion business, the other is a rounding error the CFO does not itemize. The variable is not product quality. It is who pays.
Institutional money does reach wearable makers today, but through procurement rather than reimbursement. Oura’s largest single institutional deal is a $96 million sole-source award from the Defense Health Agency for rings and a wellbeing platform across 130 military medical facilities, which Whoop protested twice. Employers and insurers run similar programs, paying for devices as a benefit or a discount.
Procurement money is real money. It also behaves nothing like reimbursement. A benefits manager renews or cancels on a budget cycle and a vibe. A billing code pays out every month a patient meets the criteria, funded by an entitlement, and it does not get cut because someone reorganized the wellness team.
Meanwhile, at the bottom of Oura’s own press releases sits the line that the ring is “not a medical device” and is not intended to diagnose, treat or monitor any condition. The company selling a health intelligence platform to public market investors has to disclaim, in its own announcements, the exact status that would let a doctor bill for it.
The Risk
The strongest counterargument to all of this launched six weeks ago, and it deserves a fair hearing.
CMS opened the ACCESS model on July 1, 2026, a ten-year voluntary payment program running through June 2035. It pays participating organizations recurring outcome-aligned payments for managing four categories of chronic condition, including hypertension, diabetes, chronic musculoskeletal pain and depression, using telehealth, wearables, apps and digital coaching. More than 150 companies and providers were provisionally approved by April. The FDA paired it with the TEMPO pilot, which offers enforcement discretion on premarket authorization for device makers who want in.
That is a genuine crack in the wall, and any wearable maker not applying is asleep. But look at the mechanics before assuming it rescues the model.
CMS pays the participating provider organization, not the device manufacturer. The wearable becomes a purchased input inside somebody else’s contract. Payment scales with the share of patients hitting outcome targets, and CMS adjusts it downward when attainment falls below half the panel. A device maker who gets inside ACCESS is no longer selling a subscription to a consumer who churns quietly at month nine. It is selling a component into a contract where the buyer carries outcome risk, audits the data, and will push that risk back up the chain at renewal.
That is a lower-margin, longer-cycle, evidence-hungry business. It is also the business Dexcom spent twenty years building, and the reason it can charge insurers instead of shoppers.
Then there is the tell hiding inside TEMPO. The pilot exists because digital health companies need FDA enforcement discretion on premarket authorization in order to participate. The industry that just won the right to skip FDA review needs a special FDA arrangement to get paid. Both things cannot stay true forever.
Two more risks sit behind that one. Consumer wearable makers are not HIPAA covered entities, which is comfortable while their data is a lifestyle product and becomes a liability the moment it drives a billable clinical decision. And Oura is carrying this unresolved question into an IPO, having filed confidentially on May 21 at an $11 billion private valuation on roughly $1 billion of 2025 revenue. Public investors will price the health care story. The prospectus will have to describe the wellness classification.
Quick Questions
Do insurers cover Apple Watch, Oura or Whoop? No. US insurers do not cover consumer wearables as a medical benefit. Some life and health insurers subsidize devices through wellness rewards programs, and HSA or FSA dollars sometimes apply, but that is a marketing spend, not clinical coverage.
Why does the FDA classification matter for payment? Medicare’s remote monitoring codes require the device to meet the FDA definition of a medical device and to transmit data automatically to the clinician. A product that sits in the general wellness category by design does not qualify, so no provider can bill for supplying it.
How much does Medicare pay for remote patient monitoring? About $52 a month for device supply and transmission, plus roughly $52 for the first 20 minutes of clinical review and $41 for each additional 20 minutes, at 2026 national average rates. Setup adds a one-time $21.71.
Did Whoop actually beat the FDA? Partly. Whoop modified its Blood Pressure Insights feature and its labeling, and the FDA then issued a closeout letter in June 2026 saying it will not enforce device requirements against the modified version. The letter covers that feature only.
Is the Oura ring a medical device? No. Oura’s own press releases state that the ring is not a medical device and is not intended to diagnose, treat, cure, monitor or prevent any condition.
Can wearable makers get paid by Medicare at all? Through the ACCESS model, indirectly. CMS pays participating provider organizations for outcomes, and those organizations can buy technology to hit their targets. The device company sells to the provider rather than billing Medicare.
The Business Model Analyst Take
Three parties could pay for a wearable: the consumer, the employer, the health system. The category built a beautiful business on the first, is winning meaningful contracts from the second, and has spent billions buying pipes into the third without securing a way to invoice it.
The FDA fight looks like a win because it was framed as freedom. What the industry bought was cost avoidance. Clearance costs money, clinical evidence costs more, and medical device liability costs most of all. Staying in the wellness lane keeps gross margins fat and the subscription model clean, which is exactly what makes the Oura IPO story legible to public investors. It also set the ceiling. Regulatory classification is a pricing decision that determines which payer you are allowed to invoice, and the wearable industry made that decision in its own favor on cost and against itself on revenue.
For founders in any regulated category, that is the transferable lesson. Ask which regulator you answer to, then ask who that answer lets you bill. If the two do not match, the integration deals and the partnerships and the data pipes are decoration.
The honest route into health care is narrow and slow, and Dexcom already walked it: clearance on a specific claim, for a specific condition, backed by outcome evidence, one indication at a time, until a payer agrees to cover it. Apple has done a version of this with atrial fibrillation. Ahmed hinted at it when he said Whoop plans to bring regulated medical technologies to market.
That path costs years and hundreds of millions, and it is the opposite of the platform moat story these companies tell. Which is why the smartest read on the next eighteen months is not whether Oura or Whoop or Apple or Google wins the wrist. It is which of them files first for clearance on a claim they could have kept selling as wellness, and eats the cost to move to the side of the line where the money is.
Based on reporting by The New York Times DealBook (Brent Crane), with regulatory and payment data from the FDA, CMS, the American Medical Association, and company filings.







