


The maker of Mounjaro and Zepbound sold its drugs cheaper, sold way more of them, and blew past every estimate. Volume is the whole strategy now.
Eli Lilly reported Q2 2026 revenue of $23.0 billion, up 48% from a year ago, and raised its full-year outlook to $85 billion to $87 billion. Adjusted earnings came in at $8.38 per share against a $6.01 consensus. Here is the part worth studying: revenue jumped 48% even though the company’s realized prices fell 13%. Volume grew 60%. Lilly is deliberately trading price for scale, and the math is working spectacularly in its favor.
Most companies protect price like it is oxygen. Eli Lilly is doing the opposite on purpose, and it just posted one of the cleanest growth quarters in Big Pharma history to prove the point. When the CEO tells you lower prices will accelerate the business, and then the numbers back him up, that is not a discount. That is a strategy.
What Happened
Lilly’s Q2 2026 print, released August 5, beat on both lines and then some. Worldwide revenue hit $22.97 billion, a 48% year-over-year increase. Non-GAAP EPS landed at $8.38, roughly $2.37 above the Street. Management lifted full-year revenue guidance by $3 billion at both ends of the range, to $85 billion to $87 billion, and the stock traded up more than 5% before the open.
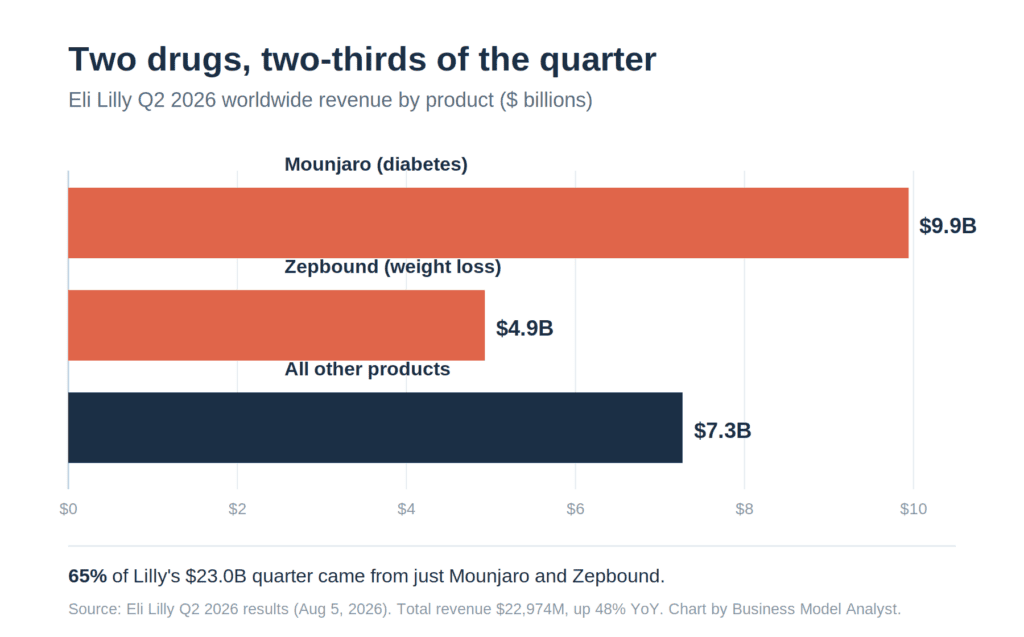
The engine is two drugs. Mounjaro, the diabetes version of tirzepatide, brought in $9.9 billion worldwide, up 91%. Zepbound, the same molecule sold for weight loss, added $4.9 billion in the U.S. alone, up 44%. Together those two products accounted for about 65% of the entire quarter. Everything else Lilly sells, from cancer drugs to immunology, made up the other third.
The counterintuitive line sits inside the revenue bridge: worldwide growth of 48% was “driven by a 60% increase in volume, partially offset by a 13% decrease in realized prices.” Outside the U.S. the pattern was even more extreme, with volume up 113% against a 36% price decline. Lilly is selling a lot more medicine for less money per unit, and coming out far ahead.
The Backstory
To see why this is a business model story and not just a good quarter, rewind. GLP-1 drugs like Ozempic and Wegovy (from rival Novo Nordisk) and Mounjaro and Zepbound (from Lilly) started as diabetes treatments and became cultural phenomena once people saw the weight loss. For two years the entire category was supply-constrained: demand ran so far ahead of manufacturing that the real competition was not price, it was who could physically make enough drug.
That is the key context. When you cannot make enough of something, cutting price is pointless. You sell everything you produce anyway. So Lilly and Novo spent that period racing to build capacity rather than racing to win on price.
Now the constraint is loosening, and the strategy flips. With more supply coming online, the winning move is to drop price, pull in the enormous population of people who were priced out, and convert a niche premium product into a mass-market one. CEO David Ricks framed it directly earlier this year: he expects global GLP-1 use to climb from roughly 20 million patients at the end of 2025 to 30 million by the end of 2026. You do not add 10 million patients by keeping prices high.
The Plan
Three moves are running at once, and they reinforce each other.
Move one: trade price for volume, deliberately. The 13% price decline was not a market forcing Lilly’s hand. Zepbound’s realized price fell partly because of “previously announced reductions in cash-pay prices,” meaning Lilly chose to lower the sticker to reach people paying out of pocket. When your addressable market is measured in the hundreds of millions of overweight and diabetic adults, a smaller margin on a vastly larger base is simple arithmetic in your favor.
Move two: the pill. This quarter marked the first revenue from Foundayo (orforglipron), Lilly’s oral GLP-1, which pulled in $98 million out of the gate. That number is tiny and actually missed the roughly $103 million analysts wanted. But the strategic significance dwarfs the dollar figure. Injectables need cold-chain logistics, specialized pens, and complex sterile manufacturing. A pill can be made and shipped at the scale of ordinary tablets, taken without food or water restrictions, and pushed through primary-care channels globally. The injectable was the premium beachhead. The pill is the distribution unlock.
Move three: recycle the cash into the next act. Lilly is plowing its GLP-1 windfall into two things: capacity and pipeline. It committed another $4.5 billion to Indiana manufacturing, and it went on an acquisition spree, closing deals for Orna, Ajax, Centessa, and Kelonia, plus three infectious-disease buys and an agreement for AtaiBeckley. Internally, its next-generation obesity drug retatrutide now has a complete Phase 3 data package, with an FDA filing planned for early 2027.
The Business Model Angle
Here is the teardown. Lilly is running a scale-and-reinvest flywheel that looks less like traditional pharma and more like a consumer-platform playbook.
Traditional Big Pharma logic is: patent a molecule, price it as high as the market and payers tolerate, defend that price until the patent expires, extract maximum margin per prescription. Price is the lever. Volume is a constraint.
Lilly has inverted that for its obesity franchise. Volume is the lever. Price is a variable it is willing to give up. The bet is that the GLP-1 category is so enormous, and Lilly’s manufacturing lead so real, that the company wins by making the market bigger rather than by squeezing more out of each sale. Lower price expands the funnel, the oral pill widens the pipe, new manufacturing capacity feeds it, and the profits buy the next generation of drugs before the current ones mature. Each piece makes the others stronger.
Notice what this requires that most drugmakers do not have: the ability to manufacture at genuinely massive scale. That $4.5 billion Indiana commitment is not a footnote, it is the moat. In a world where price is falling on purpose, the company that can make the most doses at the lowest cost wins. Gross margin actually expanded this quarter to 86.3%, because better production economics and product mix more than offset the lower prices. That is the flywheel proving itself: scale is lowering unit costs faster than Lilly is lowering prices.
The Risk
The bull case is loud, so here is the honest other side.
Concentration. Two drugs are 65% of revenue, and they are the same molecule (tirzepatide) sold under two names. Any safety signal, manufacturing disruption, or reformulation setback hits both at once. This is a spectacular franchise resting on a narrow base.
Price is a one-way street. Trading price for volume works while volume compounds. The moment volume growth slows, the price cuts stop being a growth strategy and start being pure margin erosion. Lilly is betting the patient-count curve keeps climbing steeply. If GLP-1 adoption plateaus sooner than the 30-million target implies, the model gets uncomfortable fast.
The M&A bill is real. Those acquisitions carried a $3.03-per-share acquired-IPR&D charge this quarter, which is why raised guidance still landed at $35.50 to $36.50. Buying your next act is not free, and not every acquired pipeline pays off. The “recycle cash into deals” move is a bet that Lilly can pick winners, and pharma history is littered with expensive pipeline buys that went nowhere.
Competition and policy. Novo Nordisk is not standing still and has its own oral semaglutide. Meanwhile Medicare began covering obesity drugs in July 2026, which is a demand tailwind but also drags Lilly deeper into government price negotiation, where the pricing power flows the other way. The company’s own filing flags “the implementation of the company’s voluntary agreement with the U.S. government related to drug pricing” as a live risk.
Quick Questions
Did Lilly actually cut prices, or did insurers force it? Both, but the cash-pay reductions were Lilly’s own choice, aimed at expanding the market.
Is the Foundayo pill a flop? No. It missed a small first-quarter estimate but the strategic value is in scalable distribution, not the opening $98 million.
Why did raised guidance still look modest? A $3.03-per-share charge from Q2 acquisitions offset most of the $2.78 underlying earnings upgrade.
Who is the real competitor? Novo Nordisk, the maker of Ozempic and Wegovy, especially as the battle shifts to oral GLP-1 pills.
The Business Model Analyst Take
The headline everyone will read is “earnings beat.” The lesson worth keeping is subtler: Eli Lilly is deliberately giving up pricing power because it has something more valuable, which is a market it can grow faster than it shrinks its margins. That only works if two things are true at once, a genuinely gigantic addressable market and a manufacturing advantage rivals cannot quickly copy. Lilly currently has both, which is why the flywheel is spinning.
For founders and operators, the transferable idea is this. Discounting is usually a sign of weakness, a company defending share it cannot hold on merit. But when your constraint is supply rather than demand, and your addressable market is many times your current customer base, cutting price is not surrender, it is a growth accelerant that also happens to raise the barrier for anyone without your cost structure. The trick is knowing which situation you are actually in. Most companies that cut price are in the first one and tell themselves they are in the second. Lilly, for now, is genuinely in the second. The quarter to watch is the one where volume growth finally cools, because that is when we find out whether this was strategy or just a very large tailwind.







